In adult patients with relapsed or refractory (R/R) mantle cell lymphoma
ZUMA-2 (Study 1): the longest follow-up of any study of CAR T-cell therapy in R/R MCL1,2
ZUMA-2*: a phase 2, single-arm, open-label, international study1,3
Pivotal study design (Cohort 1: BTKi-exposed patients)1,3
previously treated patients
with R/R MCL
enrolled and leukapheresed
patients received
lymphodepleting chemotherapy
and TECARTUS®†
Primary efficacy endpoint:
ORR
Selected secondary endpoints:
DOR, PFS, OS, and safety
Pivotal study design (Cohort 1: BTKi-exposed patients)1,3
previously treated patients
with R/R MCL enrolled and leukapheresed
patients received
lymphodepleting chemotherapy
and TECARTUS®†
Primary efficacy endpoint:
ORR
Selected secondary endpoints:
DOR, PFS, OS, and safety
- 60 of the 68 patients who were infused were followed for at least 6 months after their first objective disease response and were evaluable in the efficacy analysis1‡
- Bridging therapy between leukapheresis and lymphodepleting chemotherapy was permitted to control disease burden1,3
Select key inclusion criteria1,3§
- Age 18 or older
- R/R MCL previously treated with anthracycline- or bendamustine-containing chemotherapy, anti-CD20 monoclonal antibody therapy, and a BTKi (ibrutinib or acalabrutinib)
- Disease progression after the last regimen or refractory to the most recent therapy
Select key exclusion criteria1,4§
- Prior allogeneic HSCT, CAR T, and CD19-based therapies
- Active or serious infections
- Detectable cerebrospinal fluid malignant cells or brain metastases, and any history of CNS lymphoma or CNS disorders
†Following a lymphodepleting chemotherapy conditioning regimen of cyclophosphamide 500 mg/m2 intravenously and fludarabine 30 mg/m2 intravenously, both given on the fifth, fourth, and third day before treatment, TECARTUS was administered to patients as a single intravenous infusion at a dose of 2 × 10⁶ anti-CD19 CAR T cells/kg (maximum permitted dose: 2 × 10⁸ cells).1
‡Among the 60 efficacy-evaluable patients, 2 x 10⁶ CAR-positive viable T cells/kg were administered to 54 patients (90%). The remaining 6 patients (10%) received doses of 1.0, 1.6, 1.8, 1.8, 1.9, and 1.9 x 10⁶ CAR-positive viable T cells/kg.1
§See US Prescribing Information for all inclusion and exclusion criteria.
Studied in BTKi-naïve patients
Confirmatory study design (Cohort 3: BTKi-naïve patients)1,3
previously treated patients
with R/R MCL
enrolled and leukapheresed
patients received
lymphodepleting chemotherapy
and TECARTUS®†
Primary efficacy endpoint:
ORR
Selected secondary endpoints:
DOR, PFS, OS, and safety
Confirmatory study design (Cohort 3: BTKi-naïve patients)1,3
previously treated patients
with R/R MCL enrolled and leukapheresed
patients received
lymphodepleting chemotherapy
and TECARTUS®†
Primary efficacy endpoint:
ORR
Selected secondary endpoints:
DOR, PFS, OS, and safety
- The 86 patients who were infused were followed for at least 6 months after their first objective disease response and were evaluable in the efficacy analysis
Select key inclusion criteria1§
- Age 18 or older
- ≤5 prior treatment regimens
Select key exclusion criteria1§
- Prior BTKi treatment
†Following a lymphodepleting chemotherapy conditioning regimen of cyclophosphamide 500 mg/m2 intravenously and fludarabine 30 mg/m2 intravenously, both given on the fifth, fourth, and third day before treatment, TECARTUS was administered to patients as a single intravenous infusion at a dose of 2 × 10⁶ anti-CD19 CAR T cells/kg (maximum permitted dose: 2 × 10⁸ cells).1
‡Among the 60 efficacy-evaluable patients, 2 × 10⁶ CAR-positive viable T cells/kg were administered to 54 patients (90%). The remaining 6 patients (10%) received doses of 1.0, 1.6, 1.8, 1.8, 1.9, and 1.9 × 10⁶ CAR-positive viable T cells/kg.1
§See US Prescribing Information for all inclusion and exclusion criteria.
TECARTUS was studied in a range of patients with R/R MCL—a historically difficult-to-treat population1,5
Key characteristics of ZUMA-2* (Cohort 3, n=68)3
- Patients had a median of 3 prior therapies3
Key characteristics of ZUMA-2* (Cohort 3, n=68)1,6


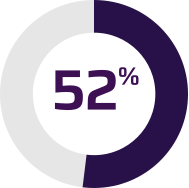
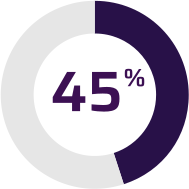
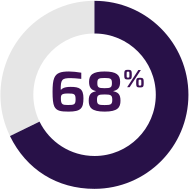
- Patients had a median of 1 prior therapy1
High-risk characteristics‡ were common in patients enrolled in the registration trial3
*The ZUMA-2 trial corresponds to Study 1 in the US Prescribing Information; see Section 14.1 on page 22.
§These characteristics were deemed high-risk in the ZUMA-2 trial. TP53 mutation and Ki-67 index ≥30% rates were based on patients with evaluable samples (n=36 and n=49, respectively). Please see the USPI for additional patient characteristics.3,6
ASCT=autologous stem cell transplant; BTKi=Bruton tyrosine kinase inhibitor; CAR=chimeric antigen receptor; CD=cluster of differentiation; CNS=central nervous system; DOR=duration of response; HSCT=hematopoietic stem cell transplant; MCL=mantle cell lymphoma; ORR=objective response rate; OS=overall survival; PFS=progression-free survival; USPI=United States Prescribing Information.
References: 1. TECARTUS® (brexucabtagene autoleucel). Prescribing Information. Kite Pharma, Inc; 2026. 2. Wang M, Munoz J, Goy A, et al. Three-year follow-up of KTE-X19 in patients with relapsed/refractory mantle cell lymphoma, including high-risk subgroups, in the ZUMA-2 study. J Clin Oncol. 2023;41(3):555-567. 3. Wang M, Munoz J, Goy A, et al. KTE-X19 CAR T-cell therapy in relapsed or refractory mantle cell lymphoma. N Engl J Med. 2020;382(14):1331-1342. 4. Wang M, Munoz J, Goy A, et al. KTE-X19 CAR T-cell therapy in relapsed or refractory mantle cell lymphoma – study protocol. N Engl J Med. 2020;1-47. 5. Kumar A, Sha F, Toure A, et al. Patterns of survival in patients with recurrent mantle cell lymphoma in the modern era: progressive shortening in response duration and survival after each relapse. Blood Cancer J. 2019;9(50):1-10. 6. van Meerten T, Kersten MJ, Iacoboni G, et al. Brexucabtagene autoleucel for BTKi-naive relapsed/refractory mantle cell lymphoma: primary analysis of ZUMA-2 cohort 3. Blood. 2026;147(12):1302-1314. doi:10.1182/blood.202502973